




Volume 7

Therapeutic Considerations

One-Step Initiation and Relapse Reduction With UZEDY in Schizophrenia

NOVEMBER 2026 | 8 MIN READ

UZEDY Therapeutic Considerations hero

Selecting an LAI

Schizophrenia is a chronic and debilitating psychiatric disorder that is associated with successive relapses.1,2 Each relapse adds an additional biological toll on the patient, including functional decline, increased treatment resistance, and progressive brain atrophy. For these reasons, targeting common drivers of relapse is a crucial goal of schizophrenia treatment.3

Nonadherence has been identified as one of the main risk factors contributing to relapse in schizophrenia. Nonadherence affects as many as two-thirds of patients with schizophrenia, and addressing it can be a challenge.4 With oral treatments, it can be difficult to identify if—and to what extent—a patient has been adherent to their daily medications until after psychotic symptoms emerge.5

LAIs can help to address this adherence gap by removing the need for patients to take a daily antipsychotic and making it clear to clinicians when a patient has missed a dose.6,7 The current LAI landscape includes a number of options that deliver different molecules and additional features.8 Clinician and patient discussions of LAIs are often tied to practical, day-to-day administration details. The effects of these differences on patients are important when selecting an LAI.7 UZEDY is a treatment option that offers an array of features that both clinicians and patients may prefer when selecting an LAI.9

UZEDY: Streamlined Initiation, Flexible Dosing, and Subcutaneous Administration

The streamlined initiation of UZEDY is possible because it utilizes the copolymer drug-delivery technology of SteadyTeq™ to control the release of risperidone in two phases—an initial release of risperidone, allowing patients to reach therapeutic plasma concentrations within 6 to 24 hours of a single dose, followed by a phase of steady release of medication over the dosing interval.10 For patients who have never taken risperidone, tolerability must be established before starting UZEDY.11 For all other patients, initiation of UZEDY is a single injection, without the need for a loading dose or oral supplementation.9,11

UZEDY offers flexible dosing options that correspond to up to 5 mg of oral risperidone.11 Both the 1- and 2-month dosing intervals of UZEDY are available in 4 different dosage strengths, starting at a dose equivalent to 2 mg of oral risperidone (Figure 1).11 This range of dosing intervals and strengths allows UZEDY to be tailored to the individual needs and preferences of each patient.11


Figure 1. Available Dosing Interval and Dosage Strength Options for UZEDY
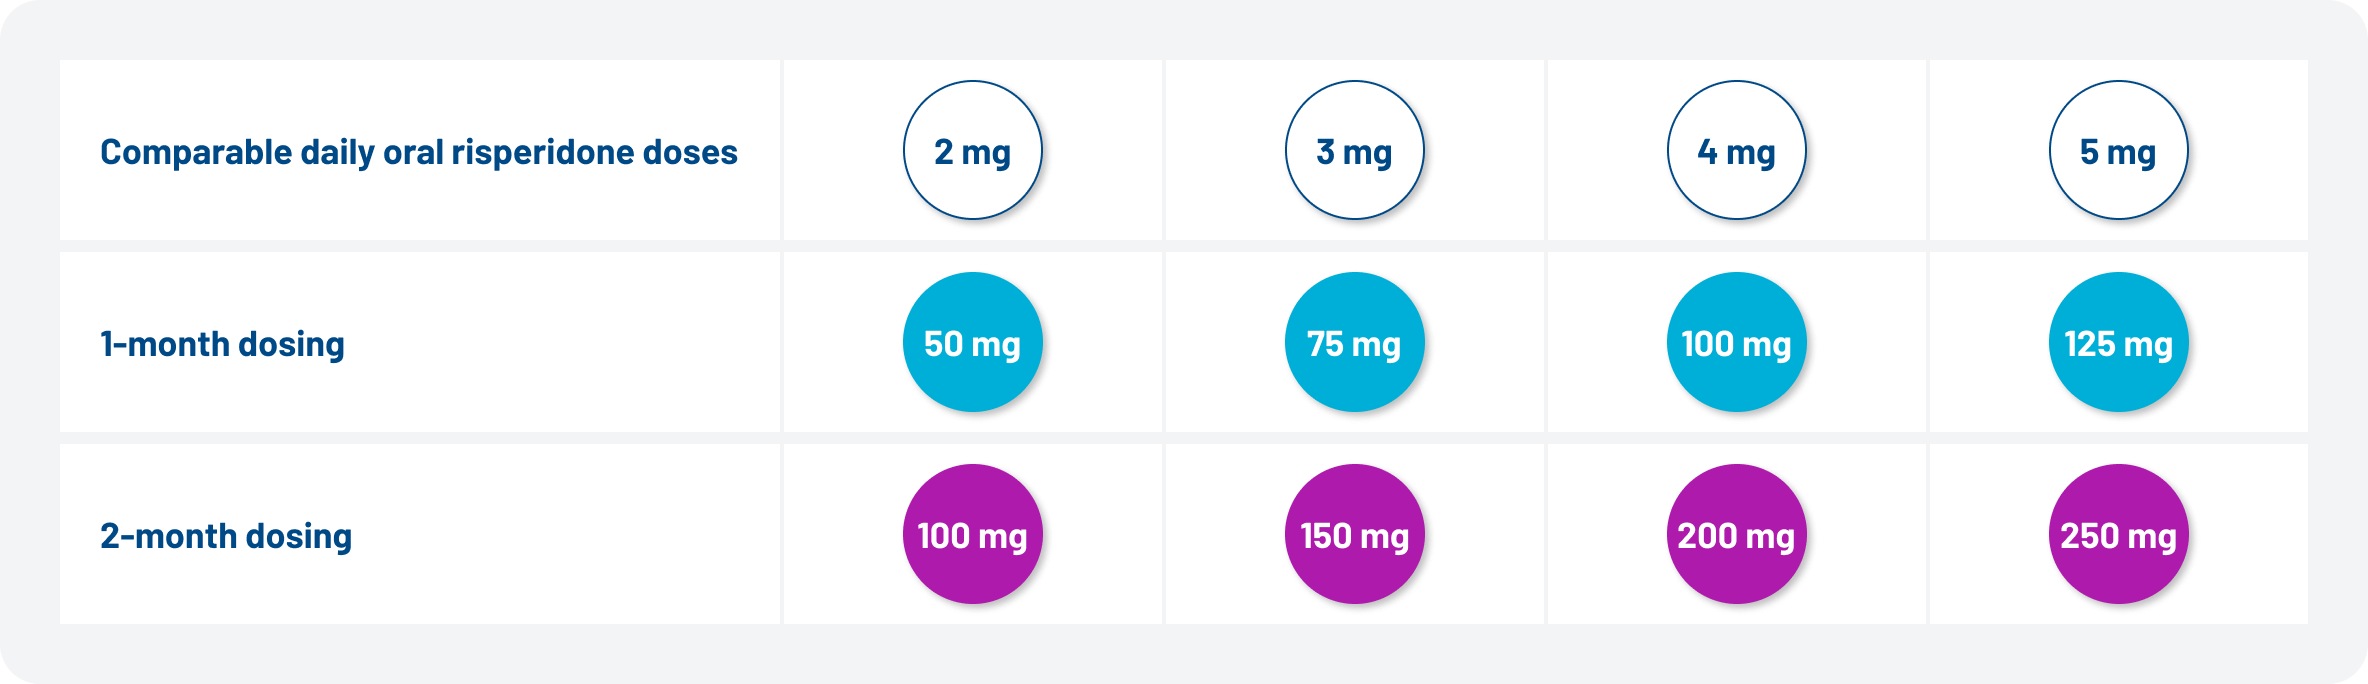
Figure 1. Available Dosing Interval and Dosage Strength Options for UZEDY

The administration of UZEDY involves a subcutaneous injection with a 5/8 inch, 21-gauge needle.11 UZEDY comes as a prefilled syringe and must be administered by a healthcare professional.11 Patients have the option of receiving an injection in the back of the upper arm or the abdomen, which allows administration to be tailored to the patient’s preference.11 UZEDY, as a subcutaneous injection, utilizes a shorter needle than the intramuscular LAIs that are currently available (Figure 2).11-17


Figure 2. Needle Sizes of Currently Available LAIs
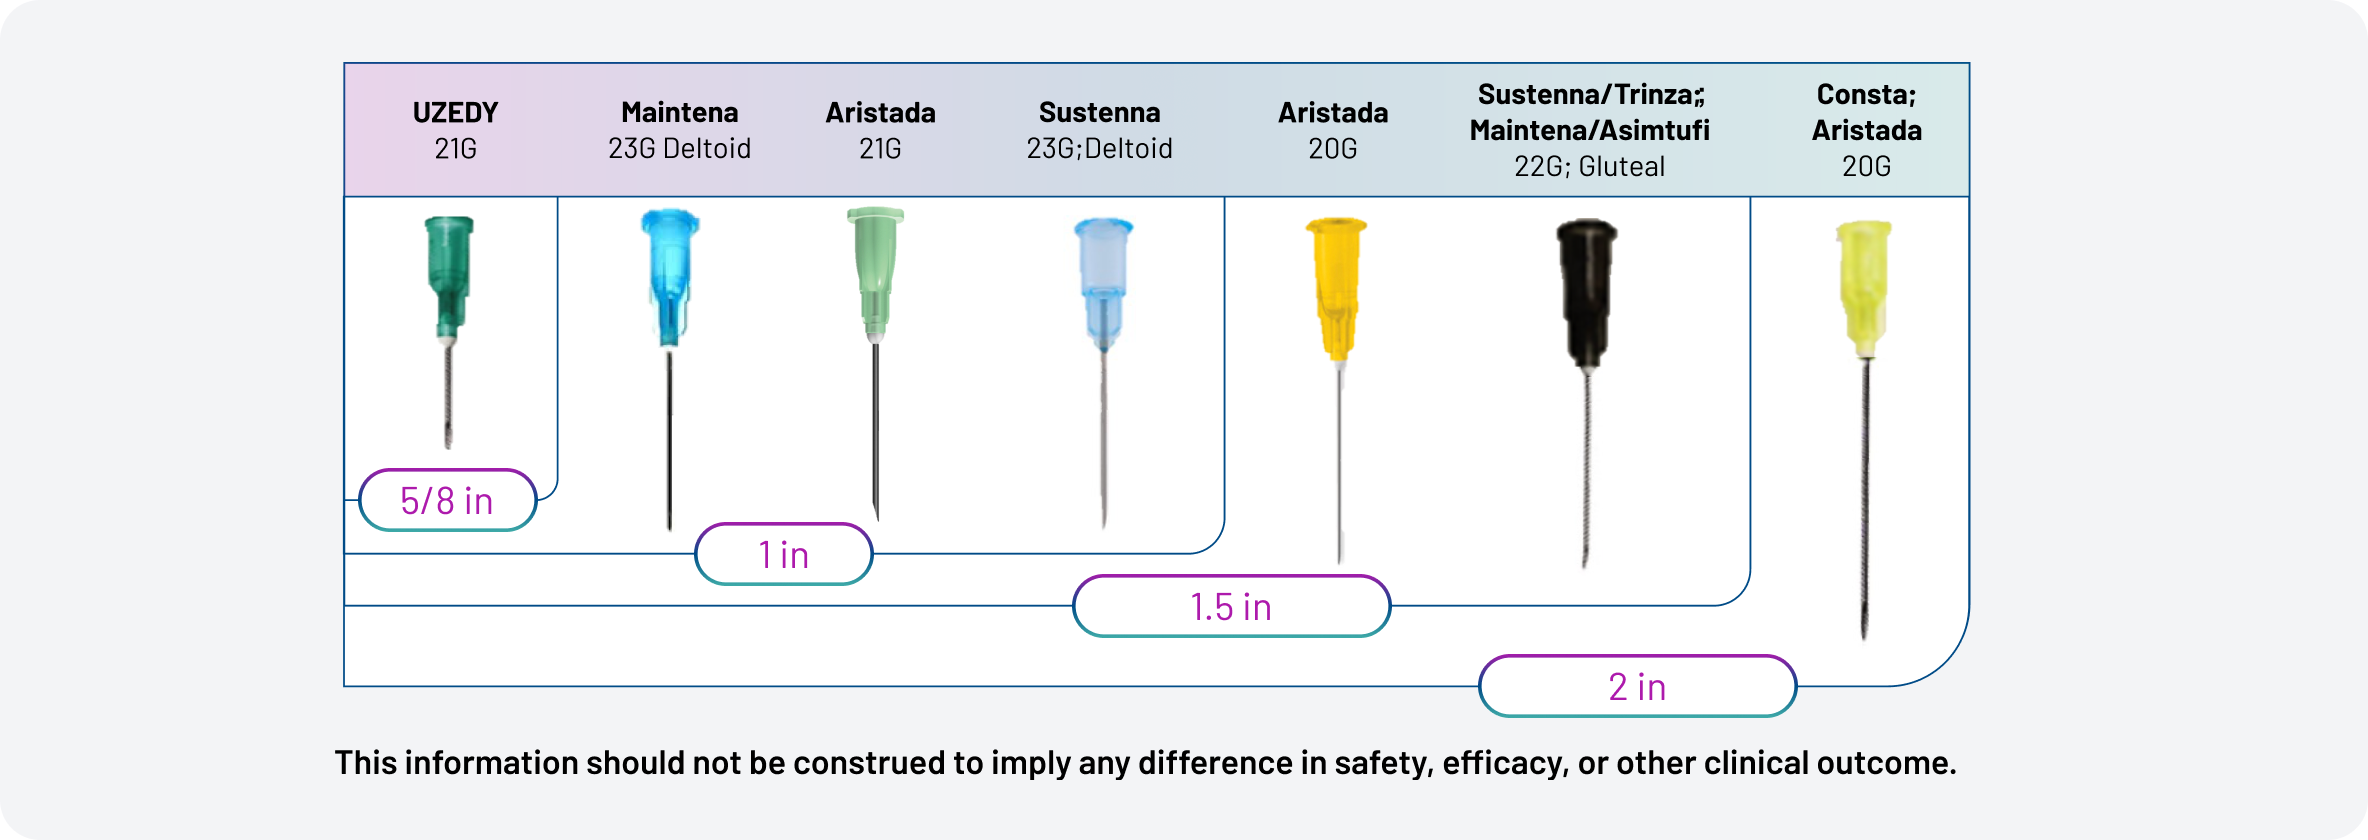
Figure 2. Needle Sizes of Currently Available LAIs
The RISE Study: Reducing the Risk of Relapse

UZEDY was evaluated in the double-blind, placebo-controlled, randomized relapse prevention study RISE, which compared UZEDY once monthly (Q1M) and once every 2 months (Q2M) with placebo in patients with schizophrenia.9 In RISE, patients receiving UZEDY Q1M demonstrated a significantly reduced risk of relapse by 80% compared with patients receiving placebo (P<0.0001) (Figure 3). In patients receiving UZEDY Q2M, the reduction in risk of relapse was 62.5%, a significant reduction compared with placebo (P<0.0001).9


Figure 3. UZEDY Significantly Reduces Risk of Relapse for Patients With Schizophrenia
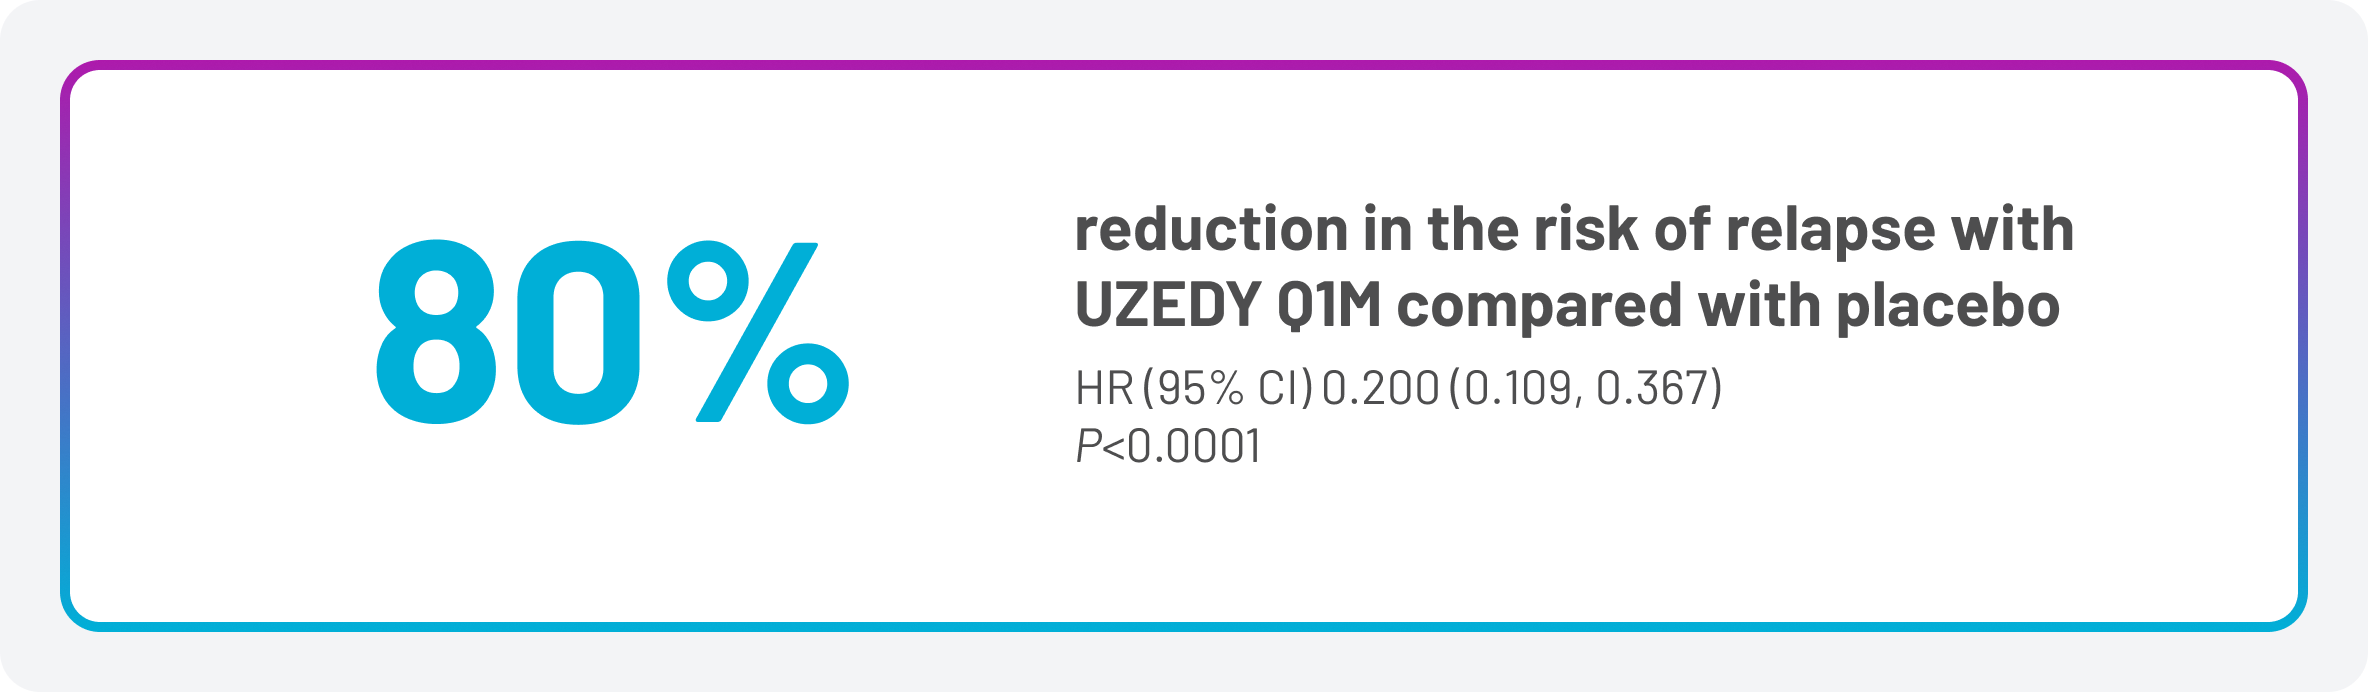
Figure 3. UZEDY Significantly Reduces Risk of Relapse for Patients With Schizophrenia

CI, confidence interval; HR, hazard ratio.

The safety profile of UZEDY in patients with schizophrenia is based on adequate and well-controlled studies of oral risperidone, which has been well-characterized. UZEDY is expected to have a safety profile similar to that of corresponding oral risperidone doses of 2 to 5 mg daily.9

Key Takeaways

UZEDY is an LAI that offers features that may benefit both clinicians and patients. The flexible dosing options of UZEDY allow clinicians to adjust their treatments while taking patient preferences for frequency of injections into consideration.11 The initiation of UZEDY—a single injection requiring no loading dose or oral supplementation—is a streamlined option that clinicians may prefer.9,11 Finally, patients may prefer a subcutaneous injection with the option to inject in the back of the upper arm or abdomen.11 Given the demonstrated efficacy and safety in combination with the features outlined above, UZEDY is a treatment option that clinicians and patients should consider when initiating an LAI.9,11


References
  1. Kane JM, Correll CU. Optimizing treatment choices to improve adherence and outcomes in schizophrenia. J Clin Psychiatry. 2019;80(5):IN18031AH1C.
  2. Alvarez-Jiminez M, Priede A, Hetrick SE, et al. Risk factors for relapse following treatment for first episode psychosis: a systematic review and meta-analysis of longitudinal studies. Schizophr Res. 2012;139(1-3):116-128.
  3. Nasrallah HA. 10 devastating consequences of psychotic relapses. Curr Psychiatry. 2021;20(5):9-12.
  4. Kaplan G, Casoy J, Zummo J. Impact of long-acting injectable antipsychotics on medication adherence and clinical, functional, and economic outcomes of schizophrenia. Patient Prefer Adherence. 2013;7:1171-1180.
  5. Masand PS, Roca M, Turner MS, Kane JM. Partial adherence to antipsychotic medication impacts the course of illness in patients with schizophrenia: a review. Prim Care Companion J Clin Psychiatry. 2009;11(4):147-154.
  6. Blackwood C, Sanga P, Nuamah I, et al. Patients’ preference for long-acting injectable versus oral antipsychotics in schizophrenia: results from the patient-reported medication preference questionnaire. Patient Prefer Adherence. 2020;14:1093-1102.
  7. American Psychiatric Association. The American Psychiatric Association Practice Guideline for the Treatment of Patients With Schizophrenia. 3rd ed. American Psychiatric Association; 2021.
  8. Correll CU, Citrome L, Haddad PM, et al. The use of long-acting injectable antipsychotics in schizophrenia: evaluating the evidence. J Clin Psychiatry. 2016;77(suppl 3):1-24.
  9. Kane JM, Harary E, Eshet R, et al. Efficacy and safety of TV-46000, a long-acting, subcutaneous, injectable formulation of risperidone, for schizophrenia: a randomised clinical trial in the USA and Bulgaria. Lancet Psychiatry. 2023;10(12):934-943.
  10. Perlstein I, Merenlender Wagner A, Gomeni R, et al. Population pharmacokinetic modeling and simulation of TV-46000: a long-acting injectable formulation of risperidone. Clin Pharmacol Drug Dev. 2022;11(7):865-877.
  11. UZEDY® (risperidone) extended-release injectable suspension Current Prescribing Information. Parsippany, NJ: Teva Neuroscience, Inc.
  12. Abilify Maintena® (aripiprazole). Prescribing Information. Otsuka America Pharmaceutical, Inc.
  13. Abilify Asimtufii® (aripiprazole). Prescribing Information. Otsuka Pharmaceutical, Inc.
  14. Aristada® (aripiprazole lauroxil). Prescribing Information. Alkermes, Inc.
  15. Invega Sustenna® (paliperidone palmitate). Prescribing Information. Titusville, NJ: Janssen Pharmaceuticals, Inc.
  16. Invega Trinza® (paliperidone palmitate) Prescribing Information. Titusville, NJ: Janssen Pharmaceuticals, Inc.
  17. Risperdal Consta® (risperidone). Prescribing Information. Titusville, NJ: Janssen Pharmaceuticals, Inc.

INDICATIONS AND USAGE

UZEDY® (risperidone) extended-release injectable suspension for subcutaneous use is indicated in adults for the treatment of schizophrenia and as monotherapy or as adjunctive therapy to lithium or valproate for the maintenance treatment of bipolar I disorder.

IMPORTANT SAFETY INFORMATION
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS

Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. UZEDY is not approved for use in patients with dementia-related psychosis and has not been studied in this patient population.

CONTRAINDICATIONS: UZEDY is contraindicated in patients with a known hypersensitivity to risperidone, its metabolite, paliperidone, or to any of its components. Hypersensitivity reactions, including anaphylactic reactions and angioedema, have been reported in patients treated with risperidone or paliperidone.

WARNINGS AND PRECAUTIONS

Cerebrovascular Adverse Reactions: In trials of elderly patients with dementia-related psychosis, there was a significantly higher incidence of cerebrovascular adverse events (e.g., stroke, transient ischemic attack), including fatalities, in patients treated with oral risperidone compared to placebo. UZEDY is not approved for use in patients with dementia-related psychosis.

Neuroleptic Malignant Syndrome (NMS): NMS, a potentially fatal symptom complex, has been reported in association with antipsychotic drugs. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status including delirium, and autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure. If NMS is suspected, immediately discontinue UZEDY and provide symptomatic treatment and monitoring.

Tardive Dyskinesia (TD): TD, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to predict which patients will develop the syndrome. Whether antipsychotic drug products differ in their potential to cause TD is unknown.

The risk of developing TD and the likelihood that it will become irreversible are believed to increase with the duration of treatment and the cumulative dose. The syndrome can develop, after relatively brief treatment periods, even at low doses. It may also occur after discontinuation. TD may remit partially or completely, if antipsychotic treatment is discontinued. Antipsychotic treatment, itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome, possibly masking the underlying process. The effect that symptomatic suppression has on the long-term course of the syndrome is unknown.

If signs and symptoms of TD appear in a patient treated with UZEDY, drug discontinuation should be considered. However, some patients may require treatment with UZEDY despite the presence of the syndrome. In patients who do require chronic treatment, use the lowest dose and the shortest duration of treatment producing a satisfactory clinical response. Periodically reassess the need for continued treatment.

Metabolic Changes: Atypical antipsychotic drugs have been associated with metabolic changes that may increase cardiovascular/cerebrovascular risk. These metabolic changes include hyperglycemia, dyslipidemia, and body weight gain. While all of the drugs in the class have been shown to produce some metabolic changes, each drug has its own specific risk profile.

Hyperglycemia and diabetes mellitus (DM), in some cases extreme and associated with ketoacidosis or hyperosmolar coma or death, have been reported in patients treated with atypical antipsychotics, including risperidone. Patients with an established diagnosis of DM who are started on atypical antipsychotics, including UZEDY, should be monitored regularly for worsening of glucose control. Patients with risk factors for DM (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics, including UZEDY, should undergo fasting blood glucose (FBG) testing at the beginning of treatment and periodically during treatment. Any patient treated with atypical antipsychotics, including UZEDY, should be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics, including UZEDY, should undergo FBG testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic, including risperidone, was discontinued; however, some patients required continuation of antidiabetic treatment despite discontinuation of risperidone.

Dyslipidemia has been observed in patients treated with atypical antipsychotics.

Weight gain has been observed with atypical antipsychotic use. Monitoring weight is recommended.

Hyperprolactinemia: As with other drugs that antagonize dopamine D2 receptors, risperidone elevates prolactin levels and the elevation persists during chronic administration. Risperidone is associated with higher levels of prolactin elevation than other antipsychotic agents.

Orthostatic Hypotension and Syncope: UZEDY may induce orthostatic hypotension associated with dizziness, tachycardia, and in some patients, syncope. UZEDY should be used with particular caution in patients with known cardiovascular disease, cerebrovascular disease, and conditions which would predispose patients to hypotension and in the elderly and patients with renal or hepatic impairment. Monitoring of orthostatic vital signs should be considered in all such patients, and a dose reduction should be considered if hypotension occurs. Clinically significant hypotension has been observed with concomitant use of oral risperidone and antihypertensive medication.

Falls: Antipsychotics, including UZEDY, may cause somnolence, postural hypotension, motor and sensory instability, which may lead to falls and, consequently, fractures or other fall-related injuries. Somnolence, postural hypotension, motor and sensory instability have been reported with the use of risperidone. For patients, particularly the elderly, with diseases, conditions, or medications that could exacerbate these effects, assess the risk of falls when initiating antipsychotic treatment and recurrently for patients on long-term antipsychotic therapy.

Leukopenia, Neutropenia, and Agranulocytosis have been reported with antipsychotic agents, including risperidone. In patients with a pre-existing history of a clinically significant low white blood cell count (WBC) or absolute neutrophil count (ANC) or a history of drug-induced leukopenia or neutropenia, perform a complete blood count (CBC) frequently during the first few months of therapy. In such patients, consider discontinuation of UZEDY at the first sign of a clinically significant decline in WBC in the absence of other causative factors. Monitor patients with clinically significant neutropenia for fever or other symptoms or signs of infection and treat promptly if such symptoms or signs occur. Discontinue UZEDY in patients with ANC < 1000/mm3) and follow their WBC until recovery.

Potential for Cognitive and Motor Impairment: UZEDY, like other antipsychotics, may cause somnolence and has the potential to impair judgement, thinking, and motor skills. Somnolence was a commonly reported adverse reaction associated with oral risperidone treatment. Caution patients about operating hazardous machinery, including motor vehicles, until they are reasonably certain that treatment with UZEDY does not affect them adversely.

Seizures: During premarketing studies of oral risperidone in adult patients with schizophrenia, seizures occurred in 0.3% of patients (9 out of 2,607 patients), two in association with hyponatremia. Use UZEDY cautiously in patients with a history of seizures or other conditions that potentially lower the seizure threshold.

Dysphagia: Esophageal dysmotility and aspiration have been associated with antipsychotic drug use. Antipsychotic drugs, including UZEDY, should be used cautiously in patients at risk for aspiration.

Priapism has been reported during postmarketing surveillance for other risperidone products. A case of priapism was reported in premarket studies of UZEDY. Severe priapism may require surgical intervention.

Body temperature regulation: Disruption of the body’s ability to reduce core body temperature has been attributed to antipsychotic agents. Both hyperthermia and hypothermia have been reported in association with oral risperidone use. Strenuous exercise, exposure to extreme heat, dehydration, and anticholinergic medications may contribute to an elevation in core body temperature; use UZEDY with caution in patients who experience these conditions.

ADVERSE REACTIONS

The most common adverse reactions with risperidone in patients with schizophrenia (≥5% and greater than placebo) were parkinsonism, akathisia, dystonia, tremor, sedation, dizziness, anxiety, blurred vision, nausea, vomiting, upper abdominal pain, stomach discomfort, dyspepsia, diarrhea, salivary hypersecretion, constipation, dry mouth, increased appetite, increased weight, fatigue, rash, nasal congestion, upper respiratory tract infection, nasopharyngitis, and pharyngolaryngeal pain.

The most common adverse reactions with risperidone in patients with bipolar disorder were weight increased (5% in monotherapy trial) and tremor and parkinsonism (≥10% in adjunctive therapy trial).

The most common injection site reactions with UZEDY (≥5% and greater than placebo) were pruritus and nodule.

DRUG INTERACTIONS

  • Carbamazepine and other strong CYP3A4 inducers decrease plasma concentrations of risperidone.
  • Fluoxetine, paroxetine, and other strong CYP2D6 inhibitors increase risperidone plasma concentration.
  • Due to additive pharmacologic effects, the concomitant use of centrally-acting drugs, including alcohol, may increase nervous system disorders.
  • UZEDY may enhance the hypotensive effects of other therapeutic agents with this potential.
  • UZEDY may antagonize the pharmacologic effects of dopamine agonists.
  • Concomitant use with methylphenidate, when there is change in dosage of either medication, may increase the risk of extrapyramidal symptoms (EPS)

USE IN SPECIFIC POPULATIONS

Pregnancy: May cause EPS and/or withdrawal symptoms in neonates with third trimester exposure. There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including UZEDY, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinicaland-research-programs/pregnancyregistry/.

Lactation: Infants exposed to risperidone through breastmilk should be monitored for excess sedation, failure to thrive, jitteriness, and EPS.

Fertility: UZEDY may cause a reversible reduction in fertility in females.

Pediatric Use: Safety and effectiveness of UZEDY have not been established in pediatric patients.

Renal or Hepatic Impairment: Carefully titrate on oral risperidone up to at least 2 mg daily before initiating treatment with UZEDY.

Patients with Parkinson’s disease or dementia with Lewy bodies can experience increased sensitivity to UZEDY. Manifestations and features are consistent with NMS.

Please see the full Prescribing Information for UZEDY, including Boxed WARNING.